Author: [AUTHOR] Published on 11/16/2026 12:00:00 AMFROM THE ASCPT ONCOLOGY COMMUNITY
QSP-Based MABEL: An Emerging Tool
By Andrew B. SyBing, Associate Director of Clinical Pharmacology & Pharmacometrics @ Pfizer Oncology
This article was initially drafted and formatted with assistance from an AI agent. The content and references were reviewed, substantially rewritten, and expanded upon to reflect my own voice and perspective.
The FDA’s June 2026 draft guidance on quantitative systems pharmacology (QSP)-based MABEL dose selection marks an important step for model-informed first-in-human oncology development. The guidance describes when mechanistic modeling may strengthen starting-dose decisions, particularly when animal translation is limited, while emphasizing model credibility, uncertainty analysis, and early clinical refinement.
IN THIS ARTICLE
The approach to first-in-human (FIH) dose selection for immuno-stimulatory agents has evolved considerably since the 2006 TGN1412 (a novel superagonist anti-CD28 monoclonal antibody) trial highlighted the limitations of relying solely on animal toxicology. In the years that followed, the minimum anticipated biological effect level (MABEL) approach became the preferred framework for many immunostimulatory therapies, including T-cell engagers and agonistic antibodies, emphasizing pharmacology and biological activity rather than toxicity alone. More recently, use of quantitative systems pharmacology (QSP) has become increasingly popular to expand the toolkit available for FIH dose selection. The FDA's 2026 draft guidance on QSP-based MABEL signals the regulatory acceptance of this model-informed strategy to balance patient safety with efficient identification of biologically active doses.
![]()
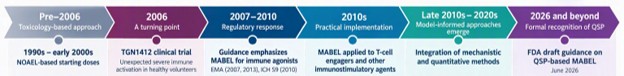
Figure 1. Timeline of FIH dose selection approaches for immune agonists Evolution from traditional toxicology-based approaches to MABEL following the TGN1412 experience, and more recently toward mechanistic, model-informed strategies incorporating QSP.
The most recent example is ISB 2001, a CD38 x BCMA x CD3 trispecific T-cell engager being investigated in relapsed or refractory multiple myeloma (RRMM). Because its CD3-binding domain does not cross-react with cynomolgus-monkey CD3, investigators could not generate a fully cross-reactive nonclinical package for human dose translation. A translational QSP model therefore integrated binding, target expression, cell abundance, pharmacokinetics, in vitro activity, mouse efficacy, and teclistamab (an approved BCMA x CD3 bispecific T-cell engager) clinical experience.
The model was developed in two stages. First, it linked ISB 2001 binding, formation of active drug-T-cell-tumor complexes, T-cell activation, cytokine release, and tumor-cell killing across in vitro systems and mouse xenograft studies. Second, the same framework was adapted to teclistamab, using matched in vitro and mouse experiments together with published human pharmacokinetic and efficacy data. This clinical benchmark was critical: in vitro activity alone markedly underpredicted the teclistamab dose range associated with clinical efficacy, whereas the mouse-informed QSP model more closely reproduced the observed teclistamab experience. The clinically anchored relationship was then translated back to ISB 2001, for which the model predicted a 10.5 µg/kg minimally pharmacologically active dose. Cytokine-release modeling refined the selected FIH target dose to 5.0 µg/kg, with simulated Cmax near the cytokine-release EC30, compared with a traditional MABEL from the EC20 of an in-vitro cytotoxicity supported a starting dose of 0.045 µg/kg, more than 100-fold lower.
For T-cell engagers, the value of QSP need not end once the first cohort is dosed. As clinical PK, cytokine, safety, and response data accumulate, the model can be updated to 1.) evaluate the dose, number (1, 2, or 3 SUDs), and interval (3-4 days, 1 week, etc.) between SUDs and 2.) explore transition to a reduced schedule that would be impractical to test exhaustively. In MM, it is common practice to transition from early intensive dosing to a less frequent maintenance dose while maintaining predicted pharmacological activity and aligning more closely with other agents used in the disease. These are prospective applications rather than established conclusions, but they illustrate how a model developed for FIH dose selection can become a longitudinal decision-support tool for dose regimen optimization.
FDA. QSP-Based Dose Selection for MABEL in First-in-Human Trials. Draft Guidance, June 2026.
- Guideline on Strategies to Identify and Mitigate Risks for First-in-Human and Early Clinical Trials with Investigational Medicinal Products (EMEA/CHMP/SWP/28367/07 Rev. 1, 2017 revision)
- International Council for Harmonisation (ICH). S9: Nonclinical Evaluation for Anticancer Pharmaceuticals. Step 5 Guideline; 2010
- Menon VCA, et al. Clinical Validation of a QSP Model for ISB 2001. Clinical Pharmacology & Therapeutics. 2026. doi:10.1002/cpt.70319.
- Chen, X. et al. Mechanistic projection of first-in-human dose for bispecific immunomodulatory P-cadherin LP-DART: an integrated PK/PD modeling approach. Clin. Pharmacol. Ther. 100, 232–241(2016).
- Afacan, N. & Chen, C. Mechanistic QSP modeling and translational strategy for determining an FIH dose for ZW171, a bispecific 2+1 T- cell engager molecule targeting mesothelin and CD3. J. Immunother. Cancer 12, 1184 (2024).
- Presler, M. et al. A quantitative systems pharmacology model for first- in- human dosing of MDX2001, a multispecific antibody for the treatment of advanced solid tumors. J. Immunother. Cancer12, 1479 (2024).
